

The Supera™ Peripheral Stent is a unique class of SFA Technology. Engineered with an innovative interwoven wire technology,
this nitinol stent offers physicians proven clinical outcomes1-12 across varied lesion complexities and lengths.1, 13-15
Results matter
The Supera™ Stent is known for the excellence of its clinical outcomes after percutaneous transluminal angioplasty (PTA) procedures with stent placement, since this peripheral stent has been studied in more than 8,000 patients and multiple studies worldwide.1,15-30*

*Nominal deployment is defined as the stent length upon deployment being within +/- 10% of the labeled stent length. This data is from a
non-powered post-hoc analysis.
non-powered post-hoc analysis.
Demonstrates excellent clinical outcomes
Supera™ Stent demonstrated excellent 1 yr patency and 3 yr freedom from TLR in the SUPERB trial.1
| 1 |
Proven clinical outcomes
|
| 2 |
Consistent patency regardless of lesion length*
|
| 3 |
Strong outcomes in calcification
|
Study reported 93.8% with Trans-Atlantic Inter-Society Consensus Document (TASC) A & B lesions and/or Rutherford class 2 or 3 lesions
*Patency rates have been evaluated in studies in lesion lengths ranging from 5.3 cm to 28.0 cm.
*Patency rates have been evaluated in studies in lesion lengths ranging from 5.3 cm to 28.0 cm.
Platform matters
Unlike any other stent design platform, the Supera™ Stent is uniquely designed to keep vessels open with its distinct platform, created by interwoven individual, flexible nitinol wires.
 |
High Compression Resistance32 4x greater strength for compression resistance—so it can maintain a round, open lumen, which can be especially beneficial in calcified lesions |
 |
Low Chronic Outward Force32 With 1:1 stent to vessel sizing, low chronic outward force results in minimal vessel injury34 |
 |
High Flexibility33 and Fracture Resistance1 Outstanding flexibility,33 which mimics the natural structure and movement of the anatomy35-37 Zero stent fractures reported at 1 year in over 8,000 patients across multiple studies1,15-30*
|

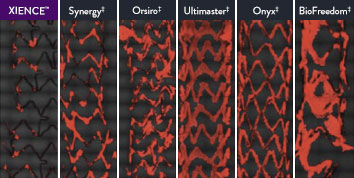
The XIENCE™ Stent is also recognized as being significantly more anti-thrombotic than other DES on the market. As shown in the study findings, XIENCE™ Stent reveals significantly less (p < 0.01) platelet adhesion—shown in red in the confocal microscopy images—than other DES, and platelet adhesion is an important factor in stent thrombosis.*8 These findings suggest that this stent choice “may be ideally suited for very short-term DAPT.”8
*Ex Vivo Swine Shunt Model.

Diamondback 360™ OAS Gives You the Versatility to Treat Challenging Cases
Treat even the most severely calcified lesions, with under 2-minute setup7,8 and predictable procedure times.2
Facilitates antegrade and retrograde treatment of:
- Long, Diffuse Lesions
Successfully treated lesions up to 60 mm in length in real-world study.9 - Heavily Stenosed Lesions
Crossed >99% of lesions with <2% pre-dilatation in the ORBIT II study.1,10 - Nodular Lesions
Effectively treats nodular calcification.5,6 - Ostial Lesions
Safely treats ostial lesions.11-13
Low Profile
6F compatible for femoral or radial access.14
Multiple Vessel Sizes
A single 1.25 mm crown treats vessels 2.5 mm to 4.0mm14
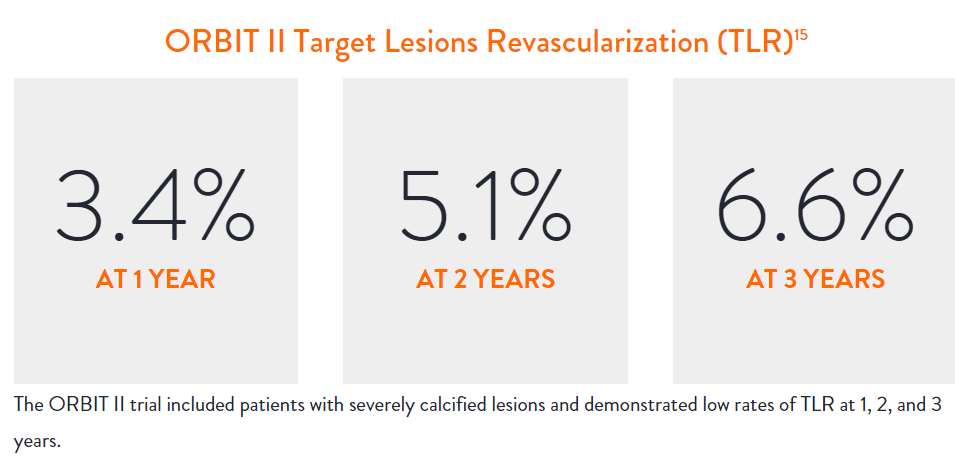
Diamondback 360™ OAS Has Been Proven Effective and Safe in the Treatment of Severely Calcified Lesions.
Extensively studied, and with over 100,000 patients treated,15 orbital atherectomy has been demonstrated to perform effectively and safely in the treatment of severely calcified lesions.
|
|
Proven Safety |
Procedural Success |
Low Q-Wave MI Rate |
>2,200 |
<1% |
97.7% |
0.9% |
|
Patients Across 11 |
Component Angiographic |
Crossing and Stent |
In the ORBIT II |
Sustained Clinical Performance
Data are for ORBIT II TLR in the OA+DES patient cohort.

STOPDAPT 2 Trial Design and Randomization10

Short 1-Month DAPT
- 0 to 1-month: Aspirin + P2Y12
- After 1-month: Clopidogrel monotherapy

12-Month DAPT
- 0 to 1-month: Aspirin + P2Y12
- 1 to 12-month: Aspirin + Clopidogrel
- 12 to 60-month: Aspirin monotherapy

- Successful PCI using CoCr everolimus-eluting stent: XIENCE™
- Eligible for DAPT (aspirin/P2Y12 receptor blocker) for 1 year

- Patients who need oral anticoagulants
- History of intracranial bleeding
- Major in-hospital complications (MI/stroke/major bleeding)
STOPDAPT Study: XIENCE™ Stent with 3-Month DAPT Is Feasible9
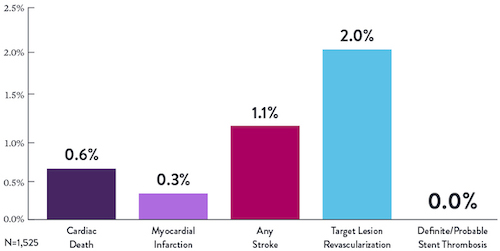
STOPDAPT9 was the first prospective trial to study DAPT cessation at 3 months after implantation. Among other 1-year outcomes, the XIENCE™ Stent rate of stent thrombosis was 0.0%.
STOPDAPT Study Demonstrates Feasibility of XIENCE™ Stent with 3-Month DAPT9
STOPDAPT-3 Trial Design and Randomization11
- PCI with planned exclusive use of CoCr-EES (XIENCE)
- ACS presentation or ARC-HBR
- Eligible for DAPT (Aspirin/P2Y12inhibitor) for 1 month
Study design and Randomization
Group 1:
0 to 1-month: Aspirin + P2Y12 (Prasugrel)
After 1-month: Clopidogrel monotherapy
Group 2:
0 to 1-month: P2Y12 (Prasugrel)
After 1-month: Clopidogrel monotherapy
STOPDAPT-3 Trial 11 was designed to explore 0-month DAPT* (SAPT˄ using only P2Y12 inhibitor) for ACS and HBR patients.
Though the results are comparable for both bleeding and ischemic events for DAPT and SAPT arms, the study did not meet its endpoint and concluded to use DAPT for 1 month after PCI.
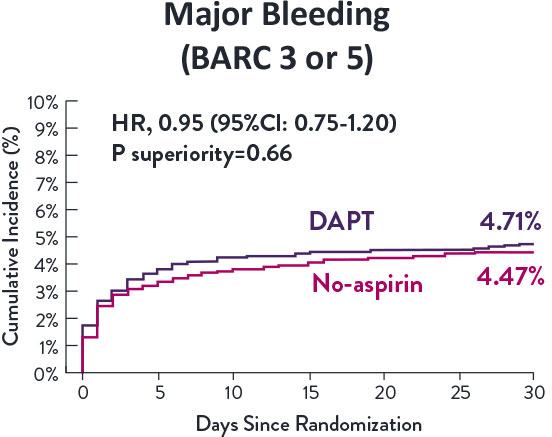
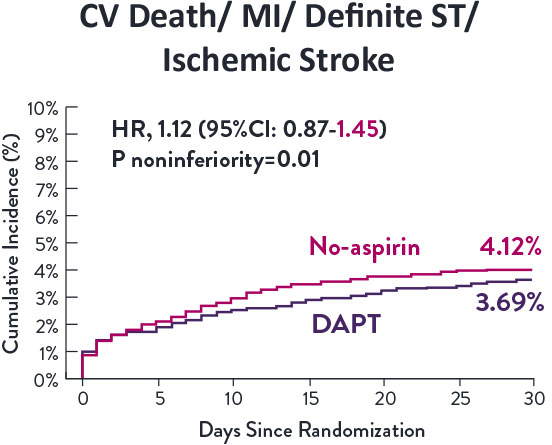

XIENCE™ Stent remains the ONLY DES with the shortest DAPT indication, as short as 28 days.12



MAT-XXXXXXX